

The Everyday Foundations Edition
Vitamin D: Understand Your Labs, Personalize Your Care
A lab-focused guide to vitamin D, genetic differences, and the hormone systems that help your body work.
Begin reading
The sunshine vitamin has a practical job
Vitamin D helps your body absorb calcium and maintain strong, properly mineralized bones. It also contributes to normal muscle, nerve, and immune function, making adequate vitamin D an important part of health. NIH ODS: Vitamin D
When there is a clinical reason to evaluate vitamin D, a blood test can help identify a deficiency and inform an individualized treatment discussion. The key is interpreting the result in context, rather than treating a supplement label or a laboratory number as a complete care plan. NIH ODS: Vitamin D
The short version: This guide focuses on lab values, not a universal daily dose. The goal is to understand your result, explore whether genetics or other health factors matter, and agree on an individualized plan with your licensed medical provider.
How it moves through your body
Your skin can make vitamin D after ultraviolet-B exposure, and foods or supplements can also supply it. NIH ODS: Vitamin D The liver converts it into 25-hydroxyvitamin D, written as 25(OH)D, and the kidneys perform much of the next conversion into its active hormone form. NIH ODS: Vitamin D
The usual test for vitamin D status is serum total 25-hydroxyvitamin D. NIH ODS: Vitamin D The active-form test, 1,25-dihydroxyvitamin D, answers different clinical questions and is generally not a good test of vitamin D stores because its level is tightly regulated and can remain normal until deficiency is severe. NIH ODS: Vitamin D
How genetic variables can affect vitamin D absorption
Genetic differences can help explain why two people do not reach the same vitamin D level on a similar routine. Studies have linked variants in vitamin D pathway genes with differences in baseline levels and the response to supplementation, although the effects of common variants are often modest and vary between studies. Randomized-trial genetic analysis 2026 genetics review
However, absorption is only one step: moving vitamin D from the intestine into the body is different from carrying it through the blood, activating it, responding to it, or breaking it down. Genetic pathways review A low blood result does not, by itself, identify which step is responsible. NIH ODS: Vitamin D
Absorption versus what happens after absorption
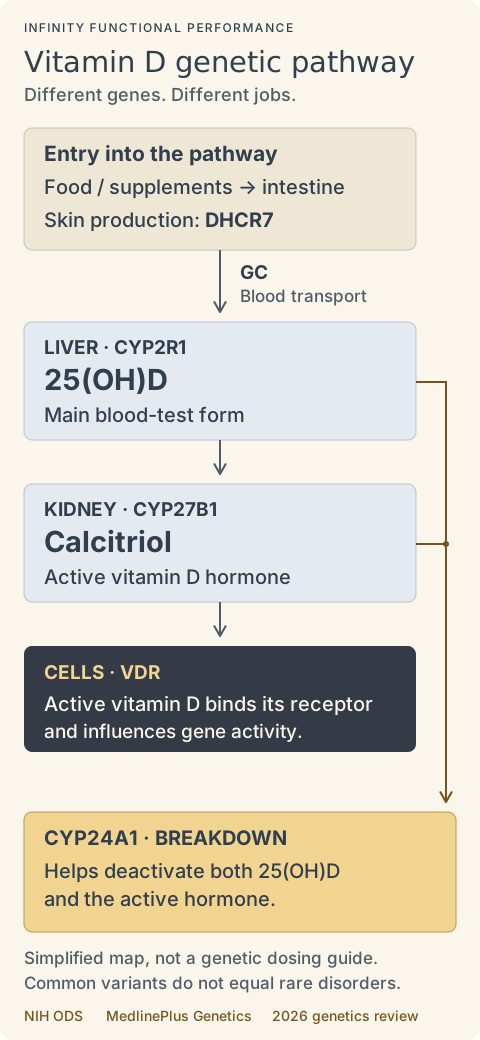
- Intestinal absorption: Proteins such as SCARB1, CD36, and NPC1L1 are being studied for their role in vitamin D uptake, but much of the evidence comes from laboratory or animal research and does not yet provide an established human genetic treatment plan. Genetic pathways review
- Skin production, DHCR7: This gene participates in the handling of a cholesterol-related precursor used to make vitamin D in the skin; it is not an intestinal absorption gene. Genetic pathways review
- Transport, GC: This gene makes vitamin D-binding protein, which carries vitamin D metabolites through the bloodstream; common variants can affect measured levels and supplementation response. 2026 genetics review
- Conversion, CYP2R1 and CYP27B1: CYP2R1 helps produce 25(OH)D, the main blood-test form, while CYP27B1 helps produce calcitriol, the active hormone. MedlinePlus Genetics
- Cellular response, VDR: This gene makes the receptor that allows active vitamin D to influence gene activity inside cells. MedlinePlus Genetics
- Breakdown, CYP24A1: This gene helps deactivate vitamin D metabolites; rare loss-of-function disorders can cause excessive vitamin D activity and high calcium rather than a need for more vitamin D. CYP24A1 clinical report
In a small study of 39 healthy men, researchers linked a combination of genetic variants to differences in vitamin D bioavailability after a test meal. INRAE research summary This supports further research into absorption differences, but it does not establish a routine genetic test that can reliably select a person's supplement dose. Genetic pathways review
Can these genetic differences be tested?
Yes, but the useful question is what the result would change. Clinical laboratories offer targeted testing and gene panels that include genes such as CYP2R1, CYP27B1, and VDR, using specimens such as blood or saliva; coverage depends on the panel selected. University of Chicago Genetic Services
There are two different kinds of information to keep separate:
- Common variants: These are frequently called SNPs, meaning small differences at particular positions in DNA. Some are associated with vitamin D levels, but current evidence does not validate routine SNP-guided dosing or a special blood target based on a common VDR or GC result alone. 2026 genetics review
- Rare disease-causing variants: These can produce specific inherited disorders of vitamin D activation or action, and identifying the cause can meaningfully change treatment. MedlinePlus Genetics Rickets treatment guidance
Rare inherited disease becomes more relevant when there is childhood-onset rickets, a suggestive family history, an unusual calcium/phosphate pattern, or persistent disease despite appropriate treatment. MedlinePlus Genetics Rickets treatment guidance Recurrent kidney stones together with unexplained high calcium and suppressed parathyroid hormone can point toward a different problem, including impaired vitamin D breakdown. CYP24A1 clinical report
For an unexpectedly low result, the evaluation should also consider supplement use, absorption conditions, medications, and kidney or liver health rather than assuming genetics is the explanation. NIH ODS: Vitamin D Depending on the findings, a specialist may add calcium, phosphate, parathyroid hormone, kidney-function or urine testing, and selected vitamin D metabolites before choosing genetic testing. Rickets treatment guidance CYP24A1 clinical report
Ask whether a reported finding is common, disease-causing, or a variant of uncertain significance, meaning its effect is not established. Uncertain variants require careful interpretation alongside the clinical findings and should not be treated as a confirmed diagnosis. CYP24A1 clinical report
How treatment changes when genetics matters
Treatment addresses the affected step, not simply the name of a gene. The examples below concern diagnosed rare disorders, not ordinary SNP findings on a wellness report. MedlinePlus Genetics Rickets treatment guidance
- Impaired CYP2R1 conversion: A specialist may use calcifediol, which is already 25-hydroxyvitamin D and bypasses the affected conversion step. Rickets treatment guidance
- Impaired CYP27B1 activation: Treatment may require calcitriol, the active hormone, or an appropriate active-vitamin-D alternative rather than relying on ordinary D3 to complete the blocked step. Rickets treatment guidance
- Rare VDR resistance: Care centers on achieving adequate calcium delivery, sometimes with specialized vitamin D treatment; response varies, and simply increasing an ordinary supplement may not overcome receptor resistance. Rickets treatment guidance
- Impaired CYP24A1 breakdown: Care may require limiting supplemental vitamin D and managing high calcium or kidney-stone risk under specialist direction, which is the opposite of automatically increasing vitamin D. CYP24A1 clinical report
Calcifediol, calcitriol, and ordinary vitamin D3 are not interchangeable products with interchangeable doses. Treatment of inherited vitamin D disorders requires monitoring that can include blood calcium, phosphate, PTH, kidney function, and urine calcium, rather than following 25(OH)D alone. Rickets treatment guidance
For a common genetic variant without a diagnosed inherited disorder, the practical approach remains interpreting the clinical picture and measured response. Genotype-based supplement formulas are still being studied and should not be presented as established treatment algorithms. 2026 genetics review
How vitamin D interacts with other hormones
Vitamin D's active form is itself a hormone, and its relationships with other hormones are not all the same. Its calcium-regulating actions are well established; findings involving reproductive, metabolic, and thyroid outcomes are more dependent on the population and outcome studied. Endotext: Calcium and phosphate homeostasis Endocrine Society guideline 2026 testosterone review
Parathyroid hormone and mineral balance
Parathyroid hormone, or PTH, helps keep blood calcium in balance: when calcium falls, PTH rises and stimulates production of active vitamin D, which helps the intestine absorb calcium. Endotext Active vitamin D also helps restrain PTH production, while another hormone, FGF23, helps regulate phosphate and reduces active vitamin D production. Endotext
This feedback system explains why a vitamin D result sometimes needs to be read alongside calcium and PTH rather than in isolation. An abnormal PTH result can have several causes, so it should not automatically be attributed to vitamin D deficiency. Endotext
Insulin and blood-sugar regulation
Vitamin D participates in processes related to insulin secretion and glucose metabolism. NIH ODS: Vitamin D For adults with high-risk prediabetes, the Endocrine Society suggests supplementation in addition to lifestyle measures to reduce progression to diabetes; this is a targeted recommendation, not proof that more vitamin D improves insulin function in everyone. Endocrine Society guideline
That recommendation does not establish a universal 25(OH)D target or a genetic dosing formula. It also does not replace nutrition, physical activity, or other indicated diabetes care. Endocrine Society guideline
Testosterone and reproductive hormones
Testosterone findings are mixed: a 2024 review found an increase in total testosterone but not free testosterone, while a 2026 review found no clear, reproducible effect on total testosterone or androgen-availability measures. 2024 testosterone review 2026 testosterone review Correcting a vitamin D deficiency may be appropriate for its own reasons, but these findings do not establish vitamin D as a reliable testosterone-raising treatment. 2026 testosterone review
The direction of a hormone change can also depend on the condition: in women with polycystic ovary syndrome, a 2023 analysis found that supplementation reduced total testosterone, with no significant improvement in the reported hair-growth score or sex hormone-binding globulin. PCOS trial review Those findings do not establish that vitamin D predictably raises estrogen or progesterone, restores fertility, or “balances hormones” in women generally. PCOS trial review
Thyroid function and thyroid autoimmunity
Vitamin D's immune effects have prompted research in Hashimoto's thyroiditis, but study results are inconsistent. Some trials report lower thyroid antibodies, while a 2024 network meta-analysis did not find a significant vitamin-D-only antibody benefit in its six-month analysis. Hashimoto's supplement review
Changes in antibody levels are not the same outcome as improved thyroid hormone production, symptoms, or reduced medication needs. This evidence does not establish vitamin D as a replacement for thyroid hormone treatment, so thyroid care and any vitamin D deficiency should be evaluated on their own merits. Hashimoto's supplement review
Start with food and an appropriate intake
Food and supplements are inputs; your blood result helps show your vitamin D status. NIH ODS: Vitamin D Absorption problems, prior gastric bypass, body size, and other health factors can affect that status, which is why the same supplement routine does not necessarily produce the same result in everyone. NIH ODS: Vitamin D
Fatty fish, fortified milk or plant beverages, and selected fortified cereals can contribute vitamin D; eggs and mushrooms provide smaller or variable amounts. NIH ODS: Vitamin D If a supplement is part of your care plan, taking it with a meal containing some fat can improve absorption, although absorption also occurs without dietary fat. NIH ODS: Vitamin D
Bring a complete list or photographs of your supplement labels to your visit. Include multivitamins, drops, calcium combinations, and stand-alone vitamin D so your provider can review the entire routine.

Should everyone have a blood test?
Testing is most useful when the result will help answer a clinical question. Situations such as low blood calcium, malabsorption, or a suspected deficiency may warrant evaluation; routine screening of generally healthy adults is a different question and is not recommended by the Endocrine Society's 2024 disease-prevention guideline. Endocrine Society: Vitamin D disease-prevention guideline (2024)
Read the result and the units together
Laboratories may report 25(OH)D in ng/mL or nmol/L: multiply ng/mL by 2.5 to obtain nmol/L. NIH ODS: Vitamin D For example, 80 ng/mL equals 200 nmol/L, whereas 80 nmol/L equals 32 ng/mL, so the units cannot be left out of a target or treatment discussion. NIH ODS: Vitamin D
The following ranges summarize the National Academies' interpretation reported by NIH; they are not a personalized prescription or a guarantee of outcomes. NIH ODS: Vitamin D
| Serum 25(OH)D | General interpretation |
|---|---|
| Below 12 ng/mL | Associated with vitamin D deficiency and risk of impaired bone mineralization. NIH ODS |
| 12 to below 20 ng/mL | Generally considered inadequate for bone and overall health in healthy people. NIH ODS |
| At least 20 ng/mL | Generally considered adequate for most healthy people; this is not permission to raise the level without an upper boundary. NIH ODS |
| Above 50 ng/mL | Linked to potential adverse effects, particularly above 60 ng/mL. NIH ODS |
Is at least 80 ng/mL an established goal?
80 ng/mL is not an established minimum for routine care or disease prevention. The Endocrine Society has not identified blood levels that provide outcome-specific prevention benefits in clinical trials, and NIH summarizes guidance to avoid levels above approximately 50–60 ng/mL. Endocrine Society guideline NIH ODS: Vitamin D
A result of 80 ng/mL does not, by itself, prove vitamin D toxicity; classic supplement-related toxicity usually involves much higher levels together with excess calcium. NIH ODS: Vitamin D However, being below a typical toxicity threshold does not establish a benefit or make that level an appropriate minimum to maintain. NIH ODS: Vitamin D If your result is around 80 ng/mL or higher, review it with your licensed medical provider rather than increasing supplements to maintain or exceed it.
Look at the clinical picture, not just one number
Vitamin D assays can differ between laboratories and methods, which can affect interpretation of an apparent change. NIH ODS: Vitamin D Bring prior results, their units, and your current supplement list, and ask whether a repeat result would meaningfully change care.
When supplementation can be especially useful
Correcting a deficiency supports normal calcium handling and bone mineralization. NIH ODS: Vitamin D People with fat-malabsorption conditions or prior gastric bypass may need particular attention because their ability to absorb vitamin D can be reduced. NIH ODS: Vitamin D
An individualized conversation can address four practical questions:
- Reason for treatment: What problem are we addressing?
- Target and boundaries: What range makes sense for my condition, and what result would prompt a change?
- Follow-up: When would another test be useful, and what would it change?
- Safety: Do my medications, calcium status, or kidney health require additional evaluation?
Some supplementation recommendations do not require a baseline test. The 2024 guideline suggests supplementation for selected groups, including adults 75 and older, pregnancy, and high-risk prediabetes, for specific potential benefits; those recommendations do not establish a target of 80 ng/mL or routine testing for everyone in those groups. Endocrine Society: Vitamin D disease-prevention guideline (2024)
D2, D3, and supplement combinations
Both vitamin D2 and D3 can raise blood levels, with D3 generally raising them more and maintaining them longer. NIH ODS: Vitamin D Ask your provider which preparation fits the reason for treatment and how your response will be assessed.
Magnesium contributes to bone health and affects active vitamin D and parathyroid hormone, while vitamin K helps proteins involved in bone metabolism function normally. NIH ODS: Magnesium NIH ODS: Vitamin K Whether additional supplements are useful is a separate discussion from choosing a vitamin D target.
Vitamin K can interact seriously with warfarin, and impaired kidney function increases the risk of magnesium toxicity. NIH ODS: Vitamin K NIH ODS: Magnesium Include combination products in the medication and supplement review.
More can become too much
Excess vitamin D from supplements can raise blood and urine calcium, with possible kidney injury and other complications. NIH ODS: Vitamin D Thiazide diuretics can increase the risk of high calcium when combined with vitamin D, particularly in people with impaired kidney function or hyperparathyroidism. NIH ODS: Vitamin D
Warning symptoms can include nausea, vomiting, unusual thirst, frequent urination, weakness, and confusion. NIH ODS: Vitamin D Seek prompt medical evaluation if these develop while taking substantial vitamin D supplements, and seek urgent care for severe symptoms.
Ask your provider whether your result or symptoms call for checking calcium and kidney function. A lab-guided plan should include an upper boundary and a reason for follow-up, not just a minimum number to exceed.
Sun exposure is not a dosing plan
Skin production varies with season, age, skin pigmentation, clothing, and other factors, so time outdoors cannot reliably predict a blood level. NIH ODS: Vitamin D Ultraviolet exposure also raises skin-cancer risk, making deliberate unprotected exposure an unsuitable prescription for reaching a laboratory target. NIH ODS: Vitamin D
The practical next step is a conversation about your health history, existing results, and whether testing or treatment would change your care. Use that discussion to build a plan you understand and can follow.
Your next step
The bottom line: Vitamin D care is about supporting health, not maximizing a test result. Bring your lab report, previous results, medications, and supplement labels to a conversation with licensed medical providers.
Infinity Functional Performance can help you explore whether an individualized evaluation is appropriate. Ask what your result means, whether a genetic test would change care, how other hormone findings fit the picture, and what follow-up would be useful; no particular test, treatment, or outcome is promised.
Visit ifp.life, call 972-619-5350, or email info@ifp.life to learn about becoming a patient.
Educational content only. This article is not a diagnosis, prescription, or substitute for individual medical advice. Do not start, stop, or adjust treatment based on a blog.
Numbered references
- NIH ODS: Vitamin D
- Endocrine Society: Vitamin D disease-prevention guideline (2024)
- NIH ODS: Magnesium
- NIH Office of Dietary Supplements: Vitamin K
- Barry et al. (2014): Genetic variants and vitamin D supplementation response in a randomized trial
- Qahtan et al. (2026): Genetic and epigenetic determinants of vitamin D metabolism
- Karrow et al. (2025): Genetic variants influencing individual vitamin D status
- MedlinePlus Genetics: Vitamin D-dependent rickets, updated 2026
- INRAE: Genetic variability and nutrient absorption, including the Desmarchelier et al. human vitamin D study
- University of Chicago Genetic Services: Hypophosphatemic rickets panel
- Haffner et al. (2022): Rickets guidance, management
- Sarvaideo et al. (2025): Hypercalcemia due to CYP24A1 variants in five unrelated patients
- Shaker and Deftos, Endotext (2023): Calcium and phosphate homeostasis
- Abu-Zaid et al. (2024): Vitamin D supplementation and male androgen outcomes
- Paez-Allendes et al. (2026): Vitamin D, testosterone, and androgen bioavailability, systematic review and meta-analysis
- Zhang et al. (2023): Vitamin D supplementation in polycystic ovary syndrome, meta-analysis
- Peng et al. (2024): Supplements in Hashimoto's thyroiditis, systematic review and network meta-analysis